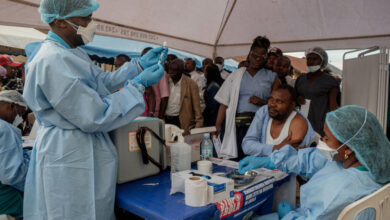
The patient, identified by an unnamed official as a diplomat, has developed multi-organ failure. Ayoade Alakija, a Nigerian physician and co-chair of a G7 committee for global health investment, noted that it took 12 days from the onset of her illness for her to be tested. This delay raised concerns about potential exposure to others. Nigerian authorities have identified 44 contacts, primarily healthcare workers, including the patient’s Swiss national husband. Officials are tracing passengers who flew with her but do not believe she was symptomatic during the journey. In 2014, a similar case detected in Lagos was brought under control within three months, resulting in 20 infections and eight deaths.
The Bundibugyo strain outbreak is currently the deadliest in the Democratic Republic of the Congo’s (DRC) recorded history. Since mid-May, the DRC has reported more than 9,000 cases and over 4,000 deaths. The virus has now affected four African nations in total as part of this specific transmission chain, with the strain becoming the DRC’s most lethal on record. The WHO states that Nigeria is the fifth country to detect the virus in this outbreak. This week, the situation widened further as Kenya reported nine cases since October 6, according to reports indicating the country is monitoring the spread closely.
Public health officials are emphasizing the cross-border nature of the crisis. Jean Kaseya, Director-General of the Africa Centres for Disease Control and Prevention, stated on social media that the outbreak is “no longer one country’s fight.” He announced plans to hold a meeting of Africa’s health ministers next week to strengthen the cross-border response and review hospital capacity. The previous West African epidemic, which ran from late 2013 to 2016, killed more than 11,000 people, underscoring the severity of the current regional threat.